Healthcare AI for Gulf Clinics: The Build Order, From Front Desk to Clinical Decisions
Automate the front desk before you touch clinical decision support. This is the build order for a Gulf clinic, what to leave alone, and how to run the numbers on your own call data.
Clinic networks that start their AI program with diagnosis usually get the order backwards. The front desk is where revenue leaks every day. Unanswered booking calls, unconfirmed appointments and manual data entry cost money now. A diagnostic assistant carries regulatory risk and may pay back years from now.
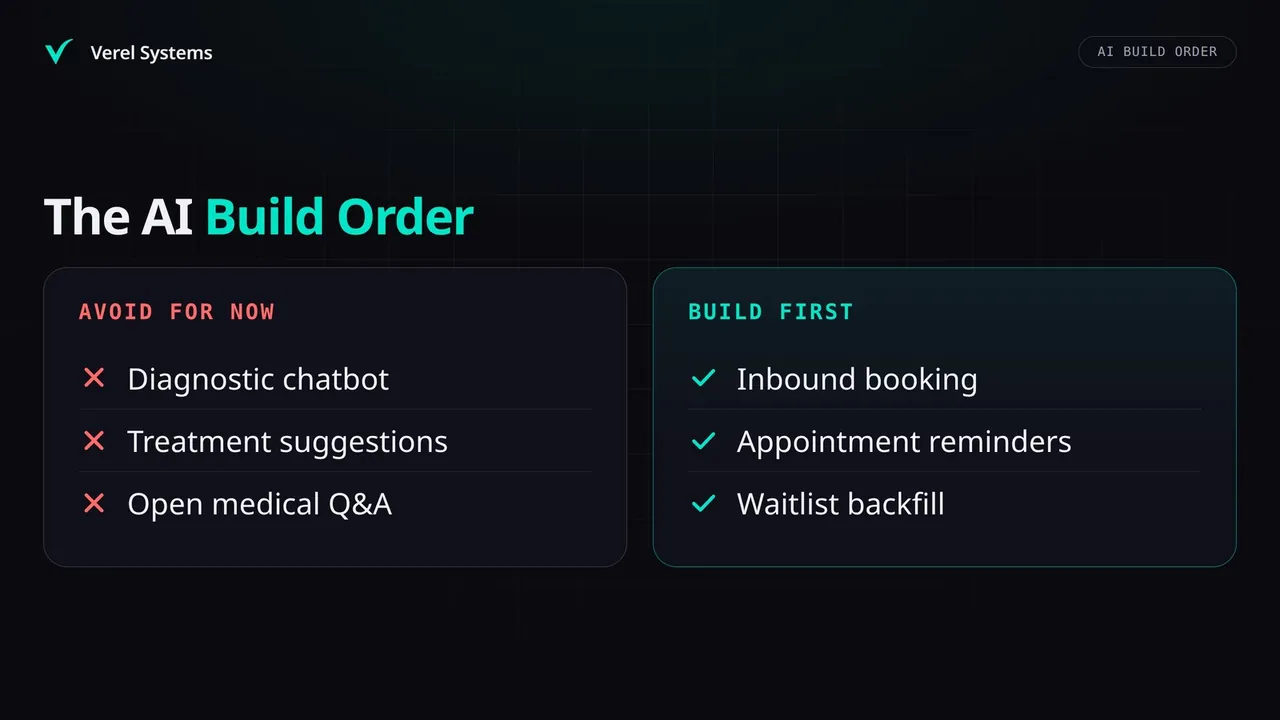
Our position is simple. Automate patient access and administration first. Keep clinical reasoning off your first-year roadmap.
The test every healthcare AI project should pass
Measure a project by one of three outcomes: staff hours saved, scheduling errors avoided, or bookings recovered. If it can't move one of them within its first quarter live, it's a research project. Research projects are fine. Just don't fund them out of the operations budget.
The second test is integration. A tool that can't read from and write to your practice management system or EMR creates work. Your staff end up copying data between screens, and the savings disappear. This is the most common reason healthcare pilots stall: the demo works and the integration never arrives. The full list is in why AI proofs of concept fail in production.
Ask any vendor one question before a demo. "Show me the appointment appearing in our scheduling system, written by your AI. No human touches it." If they can't, you're looking at a widget, not a system.
The build order: a decision table
The table below sorts common clinic workflows by the two things that decide risk and payback. Does the work need clinical judgment? Does it need to write into your core systems?
| Workflow | Clinical judgment? | System integration | Verdict |
|---|---|---|---|
| Inbound booking, rescheduling, cancellations | None | Read and write to scheduling | Build first |
| Appointment reminders with two-way rescheduling | None | Read and write to scheduling | Build first |
| Waitlist backfill when a slot opens | None | Read and write to scheduling | Build first |
| Pre-visit intake (insurance, demographics, reason for visit) | None, if it only collects | Write structured fields to EMR | Build second |
| Insurance eligibility pre-checks | None | Payer portal or clearinghouse | Build second |
| Internal SOP and protocol search for staff | Low, staff decide | Read-only document access | Build second |
| Symptom-based routing to a department | Some | Scheduling plus escalation path | Build with care, see below |
| Diagnostic chatbot for patients | High | EMR read | Avoid for now |
| Treatment or dosage suggestions | High | EMR read and write | Avoid for now |
| Open medical Q&A on your website | High, unbounded | None | Avoid |
The pattern is clear. Everything in "build first" is high-volume, repetitive and judgment-free. A wrong answer means a rebooked slot, not a harmed patient.
Inbound booking and routing
A receptionist handles one call at a time. A voice system handles calls concurrently, so the morning rush and seasonal peaks stop producing hold queues. In the Gulf, Ramadan changes call timing sharply, which is covered in planning for the Ramadan call surge.
Three requirements separate a working system from a frustrating one. It must understand Gulf Arabic dialects as well as English. It must respond fast enough to feel like a conversation, which in practice means well under a second. The latency budget for a streaming voice pipeline shows how that is met. And it must book through your scheduling system's actual availability, not guess.
Routing is the part most clinics underestimate. Every inbound call, WhatsApp message and email needs a rule: book it, answer it, or send it to a person. Verel Coordinator handles that layer: it routes inbound work under your rules, gates anything customer-facing and logs each decision.
Reminders and waitlist backfill
One-way SMS reminders tell a patient about an appointment. They rarely fix the problem when the patient can't come. A two-way reminder asks, offers a new slot, and then offers the freed slot to the waitlist. That last step turns a cancellation into a booking. The mechanics are in two-way AI appointment reminders that let the patient reschedule.
Pre-visit intake
Collecting insurance details and visit reasons before arrival moves clerical work out of the waiting room. The agent gathers answers over WhatsApp or a patient portal. It then writes them into your EMR's structured fields and flags eligibility problems early. The integration is the hard part. What each EMR allows varies widely, as covered in connecting an AI agent to your EMR.
What to avoid: clinical decision support as a first project
Large language models generate likely text. They can be grounded in your protocols, and they still make confident errors. In scheduling, an error costs a phone call. In diagnosis, it introduces significant clinical and regulatory risk.
Gulf regulators treat clinical AI accordingly. Depending on your emirate or country, that means the DHA in Dubai, DoH in Abu Dhabi and MOHAP in the UAE. In Saudi Arabia it means the Ministry of Health and the SFDA. Software that informs diagnosis or treatment can fall under medical device rules. That means approvals and clinical validation, which a first AI project should not carry. Article 6(1) of the EU AI Act treats AI used as a medical device, or its safety component, as high-risk.
Skip these in your first year:
- ▸Patient-facing diagnostic bots. Anything that tells a patient what might be wrong with them.
- ▸Treatment or dosage suggestions without a mandatory clinician sign-off built into the system.
- ▸Open medical Q&A on your website. A general model answering health questions in your clinic's name carries significant liability for minimal operational upside.
Symptom-based routing sits in between. Sending a caller to dermatology rather than orthopaedics is useful. But the system must recognise emergency language and hand off to a human every time, by rule, not by the model's judgment. We set out where that line falls in AI triage for Gulf clinic networks.
If you want knowledge-based AI early, keep it internal. A search tool that lets nurses query your approved SOPs, with citations, speeds up training and compliance. A clinician still makes every decision.
Running the economics on your own numbers
Published industry benchmarks for abandonment rates and patient value vary widely. Your own phone system already has better data. Use it. For context, a January 2023 NBER working paper estimates wider AI adoption could save 5 to 10 percent of US healthcare spending. That is a US figure and says nothing about a Gulf front desk.
Value of recovered bookings per month:
Missed or abandoned calls per month × share of those that were booking attempts × share the AI would convert × average revenue per first visit
Your telephony platform reports abandoned calls. Sample a week of recordings or callbacks to estimate the booking share. Use first-visit revenue, not an inflated lifetime value, so the case survives your CFO.
Value of backfilled cancellations per month:
Late cancellations per month × share of slots refilled from the waitlist × average visit revenue
Running cost of a voice system per month:
Total call minutes × (speech-to-text + language model + text-to-speech + telephony, all per minute) + hosting and monitoring
Get current per-minute prices from each provider. Language model cost depends heavily on how much context each turn carries, so ask for a cost per minute measured on test calls. We break down the hidden parts in our AI agent project cost breakdown.
Payback period:
Build cost ÷ (monthly recovered value + monthly staff hours redeployed × loaded hourly cost − monthly running cost)
Watch one point. Staff hours "saved" only count if you redeploy or stop hiring. If headcount stays the same and nobody's work changes, count only the recovered revenue. Our AI ROI framework walks through a complete example.
Where patient data is allowed to go
Data residency is a design decision you make on day one. Getting it wrong means rebuilding the system later.
Saudi Arabia's Personal Data Protection Law, enforced by SDAIA, treats health data as sensitive and restricts transfers abroad. In the UAE, Federal Law No. 2 of 2019 on ICT in health fields requires health data to be stored in the country, with limited exceptions. Emirate regulators add their own standards. The PDPL compliance checklist has the details.
Voice recordings and transcripts are health data too. They need the same residency care as the patient record.
Ask every vendor: "Where exactly does patient data go, and can you put that in writing?" If the answer is a US-hosted API and a shrug, keep looking.
In practice you have two routes:
- ▸In-country cloud. Use an enterprise cloud region inside the UAE or Saudi Arabia, with contracts that guarantee residency and no training on your data.
- ▸On-premise open-weight models. Run Qwen or Llama family models on your own GPU servers, behind your firewall. Patient data never leaves your network. The trade-off is hardware and operations cost, covered in our guide to on-premise LLM speed optimization.
Either way, sending identifiable patient records to a public API hosted abroad is the option to rule out.
The AI books; it does not advise, and every decision is logged in an audit trail. The other non-negotiable is a hard stop. When a caller describes chest pain or a breathing problem, the system must stop generating and transfer to a human. That rule lives in code outside the model, so a persuasive prompt can't talk the system out of it.
Frequently asked questions
Do we need to replace our EMR to use AI agents? No. Agents connect through your EMR's API, a FHIR interface, or your practice management system's booking endpoints. HL7 FHIR matters for one business reason: standard interfaces mean you can change EMR vendors later without rebuilding the AI layer. If your system has no API at all, scope that before anything else.
How long does a production patient access system take to build? It depends mostly on your EMR integration, not on the AI. A system that only answers questions can be built quickly. One that books, reschedules and writes intake data takes much longer, because every write path needs testing against real edge cases. Be wary of anyone quoting days for a fully integrated system. The MVP-to-production timeline guide explains where the time goes.
Can voice AI handle Gulf Arabic dialects? Yes, if you choose the speech-to-text engine carefully and test it on recordings from your own patients. Engines trained mainly on Modern Standard Arabic struggle with Khaleeji speech and code-switching into English. We discuss pipeline architecture in our guide to sub-500ms Voice AI. Test on your own call samples before you commit.
Start with one number this week: abandoned booking calls from last month, pulled from your phone system. If that figure, multiplied by first-visit revenue, doesn't justify a build, no AI project will. If it does, patient access is where you start.
→ AI Receptionist for Gulf Clinics: What to Automate, What Never To, and How to Price It → Connecting an AI Agent to Your EMR: What Epic, Oracle Health, TrakCare and Regional Systems Actually Allow → Two-Way Appointment Reminders at 500 Calls a Day: Pacing, Voicemail Detection, Caller ID and the Reschedule Flow