Arabic Post-Discharge Follow-Up Calls: A Khaleeji Script and the State Machine Behind It
An annotated Gulf Arabic post-discharge call, state by state, with English glosses. It covers where the AI may improvise, where it must read approved wording, and when it hands the call to a nurse.
A post-discharge call has one job. It finds the patient whose recovery is going wrong while there is still time to act. That means well before they arrive back in the emergency department.
Clinics already know this call matters. The problem is capacity. Discharge follow-ups go to the nurses who are running the ward. The calls get rushed, batched to the end of the shift, or skipped. A voice agent can make every call on schedule. But patients must stay on the line long enough to answer. And the system must know exactly when to stop talking and get a human.
Below is that call in Gulf Arabic, state by state. Dialing at volume: concurrency, retries and calling windows is a separate engineering challenge. Here the subject is what gets said once someone picks up.
Why the dialect decides whether the call works
Arabic is diglossic. Modern Standard Arabic (MSA, or Fusha) is the language of news bulletins, contracts and signage. Almost nobody uses it to ask a relative how their knee feels.
A voice agent that greets an elderly Emirati patient in MSA sounds like a government announcement. Patients treat it like an old phone menu: short answers, guarded replies, early hang-ups. For a follow-up call, a guarded answer is worse than no answer. "I'm fine" from a patient who is not fine is the exact failure the call exists to prevent.
Dialect matters on both sides of the call.
What the patient says. Gulf patients mix English medical vocabulary into Arabic all the time. An illustrative example of the pattern is: "الـ sugar اليوم عالي شوي، وأحس بدوخة". In English, that is "My sugar is a bit high today, and I feel dizzy." "Sugar" is English, "dawkha" (dizziness) is Gulf Arabic, and "shway" (a bit) is colloquial. Other patients will say the Arabic "سكر" for the same thing. The speech-to-text engine has to keep both the English term and the dialect word intact. If it normalises everything into MSA or drops the English word, the system later misreads the symptom. Google Cloud documents separate Speech-to-Text locales for Saudi Arabic (ar-SA) and Emirati Arabic (ar-AE).
What the agent says. Text-to-speech voices read what they are given. If the language model writes "الساعة العاشرة صباحاً", the voice says "at ten o'clock in the morning" in broadcast Arabic. If it writes "الساعة عشر الصبح", it sounds like a person from the clinic. So the model must generate text in dialect, spelled the way it is spoken, before the voice ever sees it. Voice choice matters too: which Arabic voice reads dialect text convincingly is a separate listening test.
"Khaleeji" is also not one dialect. "شلونك" (how are you) is natural in the UAE and Kuwait. A Najdi patient in Riyadh is more likely to expect "كيف حالك" or "وش لونك". The clinic's patient base decides the variant, and the greeting should follow the patient's region on file.
The script, state by state
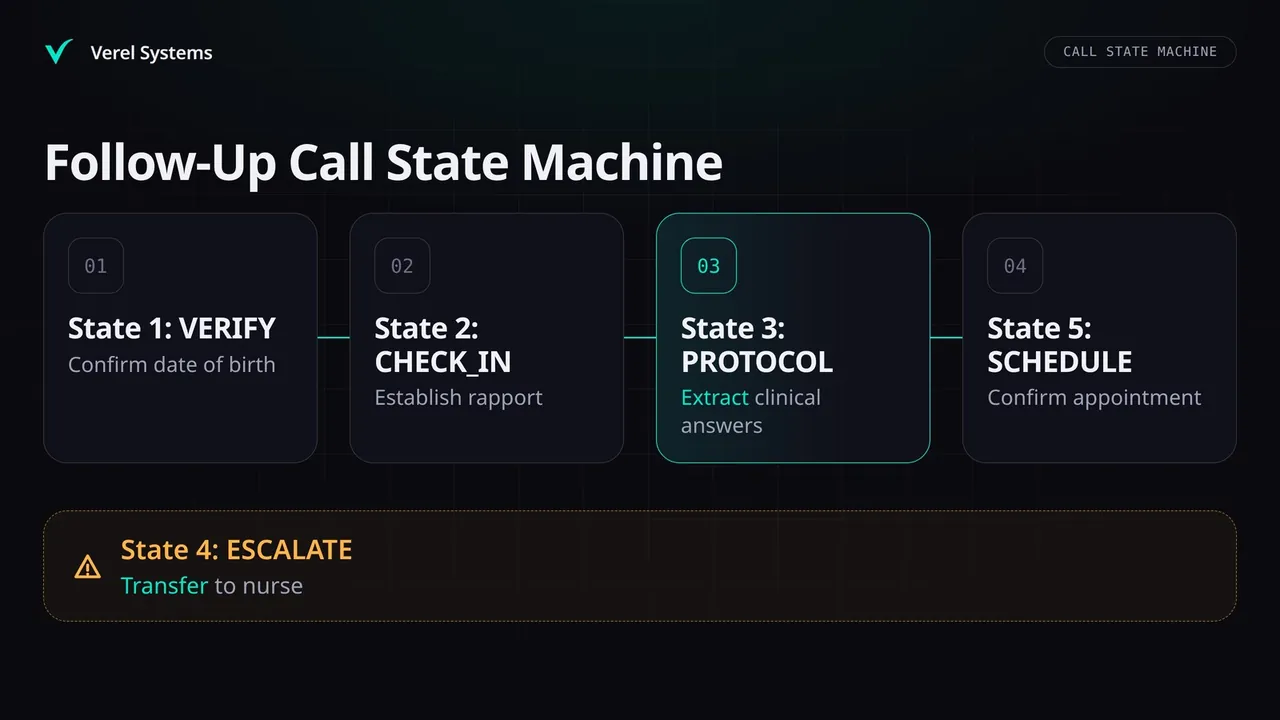
Treat a follow-up call as a state machine, not a chat. Each state has one objective, a fixed set of things the agent may say, and defined exits. The language model does two jobs: it understands what the patient meant, and it handles small talk naturally. It does not write clinical questions on the fly. Every clinical question uses wording the clinical team approved, in dialect, ahead of time.
That split is the most important design decision in the system. Freely generated clinical questions drift. One call asks about "pain", the next about "discomfort", and the answers stop being comparable across patients.
Here is an excerpt for a knee replacement patient, Emirati variant. Bracketed fields are filled from the patient record.
State 1: VERIFY
Agent: السلام عليكم، معك [اسم المساعد] من [اسم العيادة]. معاي الأخ [اسم المريض]؟ Peace be upon you, this is [assistant name] from [clinic name]. Am I speaking with [patient name]?
Patient: إيه، أنا. Yes, it's me.
Agent: الحمد لله على السلامة. عشان نتأكد بس، ممكن تعطيني تاريخ ميلادك؟ Thank God you're home safe. Just so we can confirm, could you give me your date of birth?
Transitions. If the date of birth matches, go to CHECK_IN. If someone else answers, go to PROXY_CHECK. If there is no match after two attempts, close politely and disclose nothing clinical. The agent never names the procedure before verification succeeds.
State 1b: PROXY_CHECK
In the Gulf, a son or daughter often answers for an elderly parent. The script has to plan for this. It is not an edge case.
Caller: أنا ولده، أبوي ما يقدر يتكلم الحين. I'm his son, my father can't talk right now.
Transitions. If the son is listed in the record as an authorised contact, continue with a caregiver version of each question ("How is your father's pain today?"). If he is not, the agent offers a callback time and takes a message. It says nothing about the admission. Who counts as authorised is a policy decision for the clinic, not something for the model to judge.
State 2: CHECK_IN
Agent: شلونك اليوم؟ عساك مرتاح في البيت؟ How are you today? I hope you're comfortable at home?
Patient: الحمد لله، ماشي الحال. Thank God, getting by.
This state exists for rapport. The model has some freedom here, within limits. If the patient complains about parking or billing, the agent acknowledges it, logs it for the front desk, and returns to the protocol.
State 3: PROTOCOL
Agent: من واحد لين عشرة، كم تعطي الألم في الركبة اليوم؟ From one to ten, how would you rate the pain in your knee today?
Patient: يمكن ستة، بس الركبة متورمة شوي. Maybe six, but the knee is a bit swollen.
Agent: زين إنك قلت لي. وفيك حرارة؟ Good that you told me. And do you have a fever?
Patient: إيه، أحس بحرارة من البارحة. Yes, I've been feeling feverish since yesterday.
The model's job here is extraction. From that exchange it records pain 6, swelling yes, fever yes, onset yesterday. "Since yesterday" matters: a fever starting after discharge following joint surgery is a classic escalation trigger. The model does not decide that. A rule does.
Transitions. Any escalation trigger goes to ESCALATE immediately, even mid-protocol. Otherwise, continue through the remaining questions (wound, medication, mobility), then go to SCHEDULE.
State 4: ESCALATE
Agent: سلامتك. بحولك الحين على الممرضة عشان تكلمك مباشرة. لا تسكر الخط. Get well soon. I'm transferring you now to the nurse so she can speak with you directly. Please don't hang up.
The transfer carries the structured answers and the transcript, so the nurse starts the conversation already informed. If no nurse picks up within the clinic's set window, the agent falls back to approved wording. That wording tells the patient to come in. If symptoms are severe, it says to call the ambulance number for their country (998 in the UAE, 997 in Saudi Arabia). An emergency flag also goes into the record.
State 5: SCHEDULE and CLOSE
Agent: موعد العلاج الطبيعي يوم الأحد الساعة عشر الصبح. يناسبك؟ Your physiotherapy appointment is Sunday at ten in the morning. Does that suit you?
Agent: الله يعافيك. وإذا احتجت شي، كلمنا على نفس الرقم. May God grant you good health. If you need anything, call us on the same number.
After the call, the system writes a structured result to the patient's record, typically through HL7 FHIR where the system supports it. The result includes each answer, any escalation and its reason, and the appointment outcome. What your EMR actually allows varies a lot by vendor.
The escalation rules sit outside the model
| Trigger | Source | Action |
|---|---|---|
| Fever reported after discharge | Patient answer, extracted | Transfer to nurse |
| Pain at or above the clinician-set threshold | Patient answer, extracted | Transfer to nurse |
| Wound bleeding, discharge, or spreading redness | Patient answer, extracted | Transfer to nurse |
| Chest pain or shortness of breath, any point in call | Keyword and intent detection | Transfer, plus ambulance instruction if no answer |
| Patient asks for a human | Intent detection | Transfer |
| Two failed extractions on the same question | System | Flag for nurse callback |
The clinical team sets every threshold in this table. Engineers run the rules in code, after the model's extraction. A cleverly phrased prompt cannot talk the system out of them. That is the reason a separate check outperforms a longer system prompt.
Keyword red-flag lists also fail on negation and dialect. Why negation and dialect break keyword red-flag lists explains what to use instead.
Timing: older patients pause, and the agent must wait
In human conversation, the gap between one speaker finishing and the next starting is typically around 200 milliseconds. That finding holds across languages (Stivers et al., PNAS, 2009). Voice agents that take a second or more to respond cause collisions: the patient assumes the line went quiet and starts talking again.
Post-discharge calls add a second problem. Older patients, often on pain medication, pause mid-sentence. If the system decides a patient has finished speaking too early (the setting engineers call "endpointing"), it interrupts them halfway through describing a symptom. So the tuning goes in two directions. The agent should respond fast once the patient has finished. It should also wait longer than a sales or booking agent would before deciding they have finished.
The speed side comes from streaming every stage, so the voice starts speaking before the full reply is written. Hosting close to the patient helps too. Say a call hops from Jeddah to Europe for transcription and to the US for reasoning. Distance alone eats part of its time budget. The full pipeline is in our sub-500ms voice AI post.
Where patient data is allowed to go
Hosting location is also a legal question. Two laws matter most for Gulf clinics.
Saudi Arabia. The Personal Data Protection Law treats health data as sensitive data and restricts transfers outside the Kingdom. Its penalty provisions allow fines of up to SAR 5 million under Article 36 for violations not covered by Article 35, doubled for repeat offences. Article 35 adds imprisonment for disclosing sensitive data with intent to harm. This requires strict data handling and localization for any AI system.
UAE. Federal Law No. 2 of 2019, on the use of ICT in health fields, requires health data to be stored and processed inside the country unless an exception applies. Individual emirates' health authorities add their own requirements on top.
In practice, a follow-up agent for a Gulf clinic runs either in an in-country cloud region or on the clinic's own infrastructure. When it runs on-premise, the reasoning model is typically an open-weight model from the Qwen or Llama families, served locally. Patient identifiers are kept apart from transcripts wherever the workflow allows. The decision on which law governs your deployment belongs with your counsel, not your vendor.
What to measure before you scale
Leave the vendor's ROI slide aside and use your own numbers. Weekly nurse time on follow-ups is discharges × attempts per patient × minutes per attempt, divided by 60. Clinics are often surprised by the attempts figure, because unanswered calls still cost dialing and charting time.
Then track three things in a pilot. Compare against the same patient group called by staff.
- ▸Completion rate: the share of patients who answer every protocol question. Dialect quality shows up here first.
- ▸Escalation precision: the share of transferred calls the nurse agrees needed a nurse. Too low, and the triggers waste nurse time. Zero escalations over a month means the triggers are probably broken.
- ▸Missed escalations: cases where a later chart review shows the call should have escalated and did not. This is the one number that should block a rollout.
Frequently Asked Questions
Can one system handle Saudi and Emirati patients? Yes, if the dialect is a setting per patient rather than baked into the prompt. The clinical questions are approved in each variant, and the greeting and small talk follow the region in the patient record. The escalation rules are the same in every dialect, because they run on extracted answers, not on wording.
What stops the agent from giving medical advice? Two things. First, the model does not write clinical wording. It picks from approved lines and fills in the patient's details. Second, a check outside the model reviews every reply before it is spoken, and blocks anything outside the approved set for that state. When a patient asks a medical question, the approved answer is a transfer to a nurse.
How long does a pilot take, and what should it cover? Pick one procedure with a clear protocol, such as joint replacement. Write and approve the script in the dialect your patients speak, and run it alongside staff calls for a few weeks. Don't widen the rollout until chart review shows the agent has missed no escalations.
Pick one procedure, have your clinical lead approve six questions in your patients' dialect, and time ten staff calls this week to get the baseline minutes.
→ AI Triage for Gulf Clinics: The Model Extracts, Clinician-Owned Rules Decide → ElevenLabs vs Azure Neural Voice for Arabic: Cost, Latency, and Pronunciation Control → Two-Way Appointment Reminders at 500 Calls a Day: Pacing, Voicemail Detection, Caller ID and the Reschedule Flow